
Diabetes can cause nerve damage (neuropathy) and reduced blood flow, making small cuts turn into serious wounds that are slow to heal. Our orthopedic foot and ankle specialists help protect joints, correct deformities, and restore function while coordinating vascular, wound-care, and endocrine support for true limb preservation.

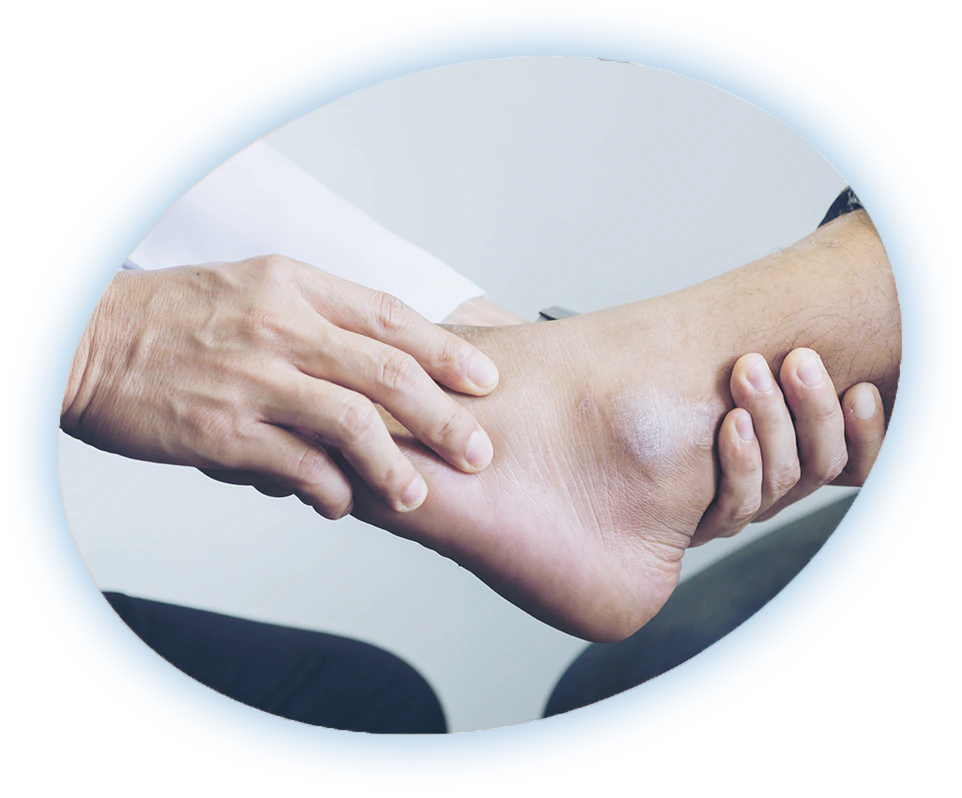
Healing a diabetic foot ulcer depends on relieving pressure, caring for the wound, controlling infection, and ensuring good blood flow.
Wound healing and protection
Minimally invasive procedures
When an ulcer keeps coming back because bone or alignment is the problem, we start with the smallest fix that truly removes pressure.

Daily habits dramatically cut the risk of foot problems. These cornerstone self-care steps are endorsed by the American Diabetes Association:
Check your feet every day
Tops, soles, and between the toes, for blisters, redness, cracks, or drainage.
Moisturize carefully
Moisturize heels but not between the toes.
Trim nails straight across
And never perform "bathroom surgery" on calluses.
Always wear socks and shoes
Protective footwear, even indoors.
Control blood glucose
Good control protects nerves and blood vessels.
Do not smoke
Smoking further reduces circulation to the feet.
Adults with diabetes should have their foot risk assessed at diagnosis and at least annually, with more frequent checks if risk is higher (neuropathy, deformity, or a prior ulcer).
For more severe problems, we step up to sturdier reconstruction to protect you long-term:
Yes, especially when pressure is truly offloaded, wound care is consistent, circulation is adequate, and infection is controlled. Non-removable offloading such as total contact casts has the strongest evidence for higher healing rates and shorter time to closure.
No. Uninfected ulcers do not typically need antibiotics. When infection is suspected, guidelines recommend deep tissue cultures after debridement and targeted therapy based on severity and organisms.
Early recognition and immobilization or offloading are crucial. Once inflammation settles, surgical reconstruction may be considered to restore a stable, braceable foot and prevent recurrent ulcers.
Adults with diabetes should have their foot risk assessed at diagnosis and at least once a year, with more frequent checks if they have neuropathy, deformity, or a prior ulcer.
Diabetes can cause nerve damage (neuropathy) and reduced blood flow. Without normal sensation, pressure and small injuries go unnoticed, and poor circulation slows healing.
Offloading means removing pressure from a wound so it can heal, using total contact casts, boots, special shoes, or inserts. It is central to healing diabetic foot ulcers.
Surgery is considered when an ulcer keeps coming back because a bone or alignment problem is causing pressure. We start with the smallest procedure that removes the pressure.
Our foot and ankle specialists provide diabetic foot care in Melbourne, Orlando (Lake Nona), and Titusville. Call (321) 499-4646 to schedule.
If you have diabetes, contact a specialist promptly for:
Hear our patients share their experience with us, All in their own words.
Expert, ultra-minimally invasive spine and orthopedic care, close to home.
Ultra-minimally invasive and endoscopic techniques
We specialize in procedures performed through incisions smaller than a dime, sparing muscle and supporting a faster recovery.
Same-day, outpatient procedures
Most patients walk in and return home within hours, rather than facing an overnight hospital stay.
Board-certified, fellowship-trained surgeons
Our team includes early leaders in endoscopic spine surgery.
A complimentary MRI review
Understand your diagnosis and options from a board-certified specialist before committing to any treatment.
Trusted by our community
More than 1,100 patient reviews at a 4.6-star average, and over 50,000 patients treated.
Coordinated care for limb preservation
We coordinate vascular, wound-care, and endocrine support alongside orthopedic foot care.
Comprehensive spine and orthopedic care
From injections to advanced procedures, your full continuum of care is handled in one place.
Convenient locations across the Space Coast and Orlando
Care close to home in Melbourne, Orlando (Lake Nona), and Titusville.